Treatments
Venous Stasis Ulcer Treatment: What a Circulation Assessment Reveals
Learn what circulation tests reveal for venous stasis ulcer treatment. Discover how ABI and ultrasound shape safe, customized compression therapy.
Published · Anchor Wound Management
Overview
- Circulation assessments identify whether blood flow challenges in your legs stem from vein dysfunction, arterial disease, or a combination of both.
- Checking the ankle-brachial index is a mandatory safety step to ensure adequate arterial blood supply before starting compression therapy.
- Venous duplex ultrasound maps backward blood flow in leg veins, pinpointing the source of sustained venous hypertension.
- Diagnostic results allow clinicians to prescribe safe, customized compression levels while protecting against complications.
When a non-healing sore develops on the lower leg, navigating effective venous stasis ulcer treatment requires looking far deeper than the surface of the skin. Many individuals assume that managing an open leg wound is primarily about finding the right topical ointment or protective dressing. While specialized dressings are essential for protecting fragile tissue and managing drainage, true progress begins with understanding the vascular forces at work beneath the surface. Blood must circulate smoothly down into the feet and return efficiently upward to the heart. When circulatory pathways encounter resistance, valve failure, or narrowing, the delicate tissues of the lower leg bear the burden. A formal circulation assessment provides the clinical roadmap necessary to determine which therapies are safe and appropriate for your specific anatomy.
Why Circulation Testing Precedes Venous Stasis Ulcer Treatment
Lower extremity wounds often arise as a direct consequence of chronic venous insufficiency, a vascular condition where veins struggle to transport deoxygenated blood back toward the chest. According to the MedlinePlus medical overview on venous insufficiency, diseased veins fail to pump blood efficiently, leading to persistent swelling, dull aching, progressive skin changes, and eventual open sores. When tiny, one-way valves inside leg veins weaken, gravity pulls blood downward, creating chronic pooling known as venous stasis.
Over time, this continuous backpressure—termed venous hypertension—stretches vein walls and forces fluid, proteins, and red blood cells into surrounding subcutaneous tissues. The skin becomes inflamed, discolored, and fragile, ultimately breaking down under minimal trauma. However, because symptoms like swelling and skin discoloration can also overlap with peripheral artery disease or lymphatic dysfunction, clinicians cannot rely on visual inspection alone. Administering therapies without objective vascular data introduces significant risks, which is why an in-depth circulatory evaluation serves as the non-negotiable starting point for personalized care.
Patients who need specialized assistance can explore comprehensive care options through our dedicated focus on chronic lower leg wounds.
The Ankle-Brachial Index: Verifying Arterial Blood Supply
The cornerstone of venous ulcer healing is therapeutic compression, which counters gravitational pressure and assists veins in pumping fluid upward. However, applying compression to a limb that lacks adequate incoming arterial blood flow can cause severe complications, including tissue necrosis. For this reason, clinical standards require performing an ankle-brachial index (ABI) before applying therapeutic wraps or garments.
An ABI compares blood pressure measurements taken at your ankles with blood pressure readings taken at your upper arms. The clinician uses a handheld Doppler ultrasound probe and an inflatable pressure cuff to listen to arterial pulse signals in the dorsalis pedis and posterior tibial arteries. By dividing the highest ankle systolic pressure by the highest brachial systolic pressure, the practitioner calculates an objective numerical ratio.
As documented in clinical research on venous leg ulcer management from StatPearls, venous ulcers represent a severe manifestation of chronic venous hypertension, and evaluating the ankle-brachial index is a vital measure to exclude underlying arterial disease before applying compression. A standard ABI reading between 0.90 and 1.30 generally indicates normal arterial perfusion, confirming that high-level therapeutic compression can be safely tolerated. A ratio between 0.60 and 0.89 indicates mild to moderate arterial disease, requiring modified, reduced compression under close supervision. An ABI below 0.50 signifies severe arterial compromise; standard compression is strictly avoided, and immediate vascular surgical evaluation is warranted.
Venous Duplex Ultrasound: Mapping Venous Reflux and Obstruction
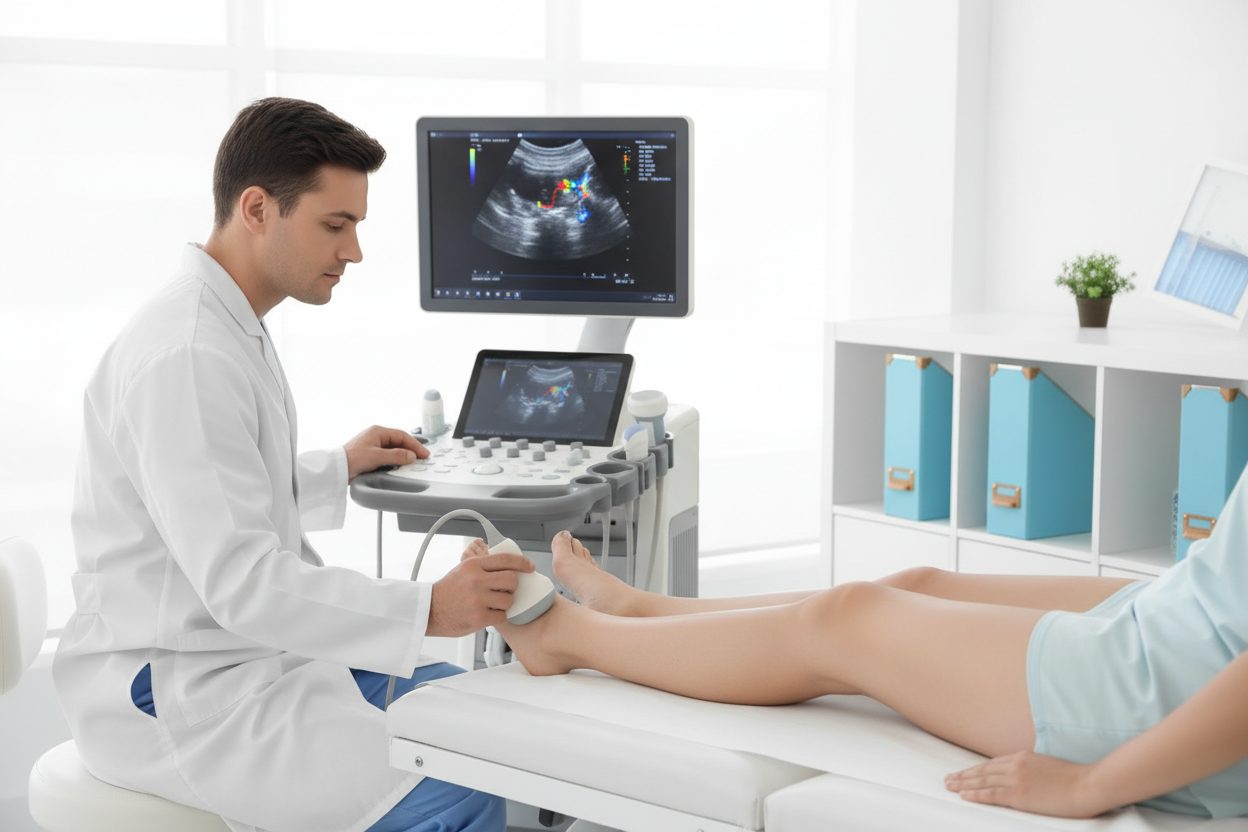
While the ABI verifies that oxygen-rich blood can reach the foot, venous duplex ultrasound examines the return pathway. This painless imaging procedure combines traditional ultrasound, which visualizes anatomical structures, with Doppler ultrasound, which assesses the velocity and direction of moving blood cells.
During an ultrasound examination, a vascular specialist evaluates deep veins inside the leg muscles and superficial veins near the skin surface. The test identifies two primary issues:
- Venous Reflux: Under normal conditions, tiny valve leaflets open to let blood travel upward and snap shut to prevent it from sliding backward. If valves fail, blood travels retrogradely (backward), creating venous reflux. The ultrasound technician measures the duration of reflux in fractions of a second to quantify valve failure.
- Venous Obstruction: The ultrasound checks whether old blood clots, deep vein thrombosis, or external anatomical compression are physically blocking venous outflow pathways.
Pinpointing whether valve failure resides in superficial veins, deep veins, or perforator veins (which connect the two networks) informs the broader medical strategy. When superficial reflux is identified, minimally invasive endovenous procedures performed by vascular specialists may help eliminate the high-pressure source, supporting long-term tissue stabilization.
How Circulation Data Dictates Compression Strategy
Once your vascular profile is clear, clinicians translate numerical findings into a personalized compression plan. Compression therapy is not a one-size-fits-all garment; it is a clinical prescription that must match your specific arterial capacity and tissue health.
For patients with normal arterial status, clinicians typically utilize multi-layer compression bandage systems or high-grade compression garments delivering 30 to 40 mmHg of pressure at the ankle. This level of continuous, graduated force reduces vein diameter, enhances valve coaptation, accelerates venous blood velocity, and forces accumulated fluid back into the lymphatic circulation. Conversely, if your assessment reveals concurrent arterial disease, high-pressure garments could cut off oxygen delivery. In those mixed-etiology cases, clinicians prescribe light, modified compression bandages (often below 20 mmHg) to manage swelling without starving the foot of essential arterial blood.
Managing extensive fluid retention often goes beyond basic wraps. Patients dealing with significant tissue swelling frequently benefit from structured specialized lymphedema therapy to systematically evacuate stagnant fluid before transitioning into maintenance compression garments.
Warning Signs and When to Seek Urgent Medical Care
Venous ulcers require consistent monitoring because compromised skin is highly susceptible to secondary bacterial infections. Patients and caregivers must remain vigilant for clinical red flags that indicate a worsening condition requiring prompt evaluation. Seek immediate medical attention if you experience:
- Sudden, severe, or escalating leg pain that is not relieved by elevation or rest.
- Spreading redness, warmth, or noticeable hardness expanding outward from the wound margins.
- Foul-smelling drainage, cloudy yellowish pus, or a sudden increase in fluid output soaking through dressings.
- Systemic symptoms, including fevers, chills, dizziness, confusion, or nausea.
- Changes in foot temperature, pale or blue toes, or numbness, which may indicate compromised arterial circulation.
Never attempt home debridement, sharp scraping, or unprescribed compression adjustments. Doing so risks exacerbating tissue trauma or causing arterial compromise.
Compassionate Wound Care Across Dallas–Fort Worth
Achieving stable wound closure requires thorough diagnostics, tailored compression protocols, and steady clinical support. For individuals who face mobility barriers or chronic exhaustion from frequent clinic trips, exploring mobile wound care visits provides high-quality diagnostic and bedside management right at home.
At Anchor Wound Management, our dedicated clinical team serves families throughout the Dallas–Fort Worth metroplex with clinic locations in Plano and Irving as well as convenient in-home appointments. If you or a loved one is struggling with an unhealed lower extremity sore or chronic swelling, contact our compassionate team today to schedule a detailed vascular assessment and begin your path toward structured recovery.
Sources
- Robles-Tenorio A, Lev-Tov H, Ocampo-Candiani J. Venous Leg Ulcer (StatPearls). 2022.
- MedlinePlus Medical Encyclopedia. Venous insufficiency.