Conditions
Burn Wound Care: When an Injury Needs Specialist Follow-Up
Wondering if your injury needs expert attention? Discover when burn wound care requires emergency care, specialist follow-up, or simple home management.
Published · Anchor Wound Management

Overview
- Severe burns involving deep tissue, broad surface area, sensitive body locations, or chemical and electrical sources require immediate emergency medical care before outpatient management.
- Minor superficial burns often heal with simple first aid at home, while partial-thickness or sluggish injuries benefit from focused outpatient evaluation.
- Persistent redness, stalled progress after ten to fourteen days, foul odor, worsening pain, or heavy drainage signal that an injury needs specialist attention.
- Specialized clinical management includes structured wound bed evaluations, advanced moisture-balancing dressings, and protective barriers to support tissue recovery while limiting complications.
A sudden thermal accident, scald, or contact injury can disrupt your daily routine in seconds, leaving painful tissue damage that feels overwhelming to manage. Understanding the right level of support is vital, whether you need immediate emergency stabilization, basic home first aid, or outpatient burn wound care to prevent chronic complications. Thermal injuries behave differently from simple cuts or scrapes because heat causes progressive cellular injury that evolves over several days. Knowing when an injury requires urgent hospital triage versus ongoing outpatient management protects healing tissue, eases discomfort, and limits functional impairment.
Emergency Care First: When to Call 911 or Visit the ER
According to the MedlinePlus medical resource on burns, serious injuries demand urgent emergency intervention rather than delayed outpatient treatment. You must seek immediate emergency medical care or call 911 if a burn is large, deep, or affects critical anatomical regions such as the face, hands, feet, groin, buttocks, or major joints. Chemical exposures and electrical shocks also mandate emergency triage because chemicals continue damaging tissue until thoroughly neutralized, and electrical currents can inflict profound internal injuries invisible on the surface.
Emergency medical teams focus on systemic stability, airway management, fluid resuscitation, and immediate pain control. Attempting to manage extensive injuries at home or waiting for an outpatient appointment can lead to life-threatening complications, including shock, dehydration, or systemic infection. Once emergency physicians stabilize the injury and rule out acute systemic dangers, individuals often transition to specialized outpatient clinics for ongoing recovery.
Understanding Burn Depths and Appropriate Care Levels
Burns are clinically categorized by tissue depth, which determines the most appropriate treatment environment.
First-Degree Burns
First-degree burns affect only the epidermis, the outermost layer of skin. Common examples include mild sunburns or brief hot liquid splashes. The skin appears red, dry, and sensitive to touch, without blister formation. These superficial injuries typically resolve within seven to ten days using cool compresses and gentle moisturizers, rarely needing clinical intervention.
Second-Degree Burns
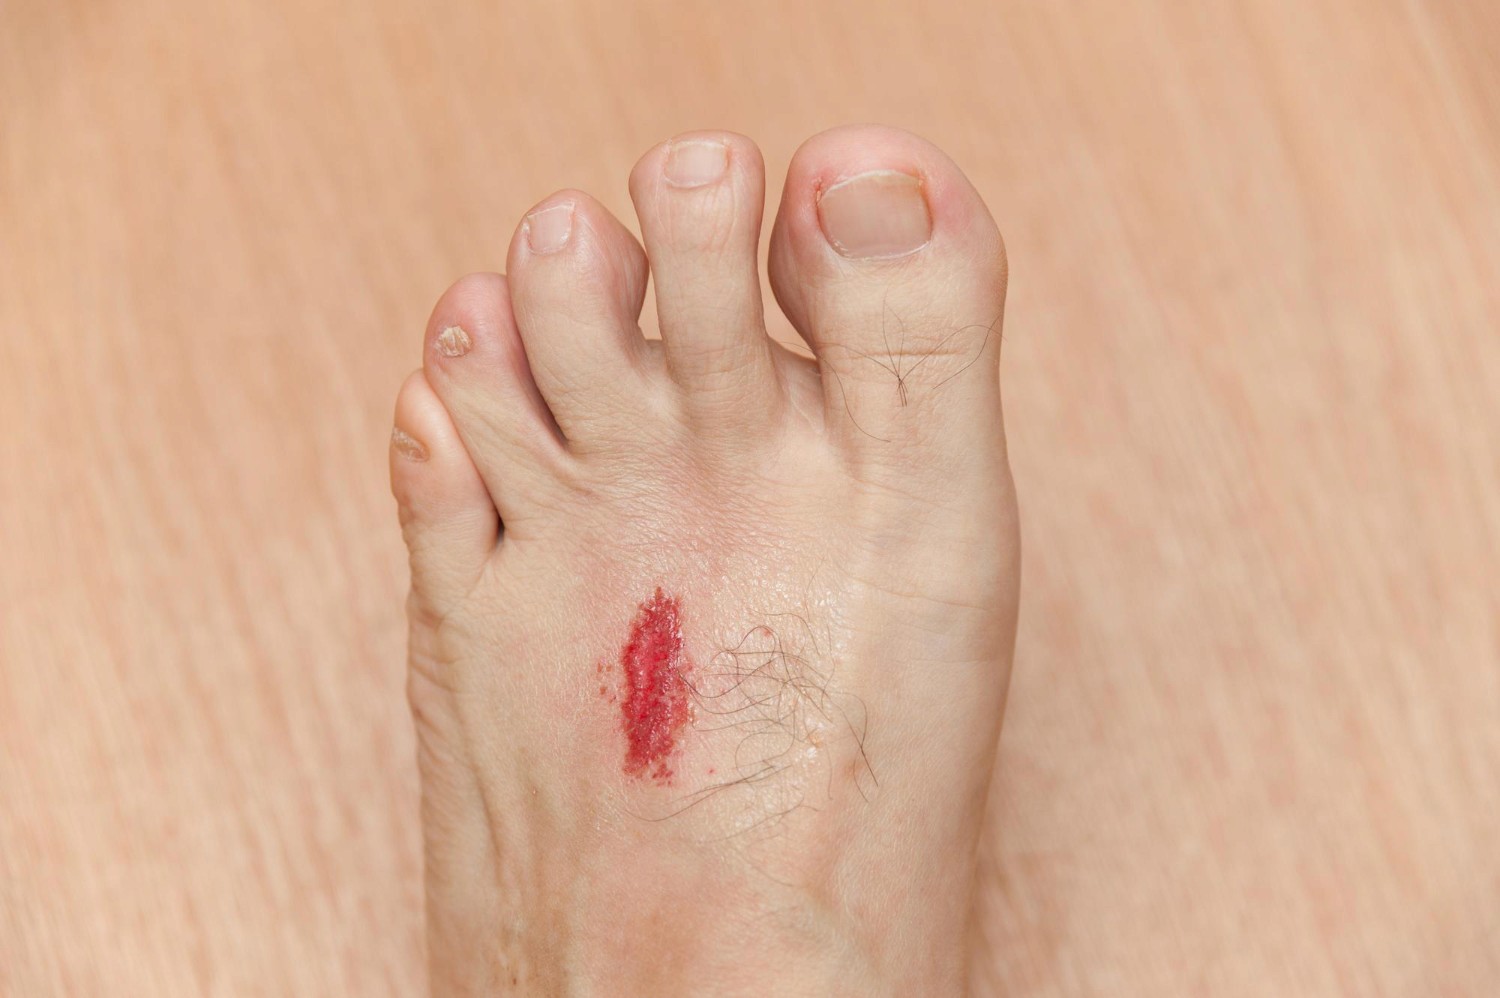
Second-degree burns, or partial-thickness burns, penetrate into the dermis beneath the epidermis. These wounds cause intense redness, notable swelling, significant pain, fluid weeping, and blister formation. MedlinePlus advises that you should never break blisters, as intact blister skin acts as a natural sterile biological cover shielding raw nerve endings and delicate lower tissue from bacteria. While minor second-degree burns may heal with gentle home hygiene, larger injuries or wounds healing sluggishly benefit from an outpatient evaluation for complex thermal injuries.
Third-Degree Burns
Third-degree burns, or full-thickness burns, destroy the epidermis and dermis completely, often reaching underlying subcutaneous fat and nerves. The damaged tissue may appear leathery, waxy white, brown, or charred. Due to destroyed nerve endings, third-degree burns may paradoxically cause little localized pain at the center, though surrounding tissue remains severely painful. These severe injuries never heal with home remedies; they always demand acute hospital stabilization followed by specialist care.
Common Home Care Mistakes to Avoid
Well-intentioned home remedies often complicate recovery. Popular folk advice frequently recommends spreading butter, cooking oil, mayonnaise, or greasy ointments across fresh burns. MedlinePlus explicitly warns that you must never apply butter, grease, or ice directly to a burn. Greases trap heat in damaged tissue, prolonging thermal damage, while oily residues attract airborne debris and harbor dangerous bacteria.
Applying ice cubes or freezing cold water is similarly counterproductive. Extreme cold causes rapid blood vessel constriction, shutting down circulation to vulnerable tissue and potentially turning a partial-thickness injury into a deeper wound. The safest immediate step is running cool, comfortable tap water over the burn for ten to fifteen minutes. Additionally, never attempt to pick at peeling skin or cut away dead tissue at home. Self-debridement without sterile clinical instruments introduces bacteria, tears fragile new tissue, and causes painful bleeding.
Signs a Burn Is Not Healing and Needs Specialist Follow-Up
How do you identify when an injury has stalled and warrants clinical evaluation? While mild superficial burns show steady re-epithelialization within a week to ten days, stubborn partial-thickness wounds often encounter obstacles. If your burn shows no visible progress after two weeks, underlying issues such as chronic inflammation, reduced local blood flow, or bacterial burden may be impeding cellular repair.
Pay close attention to signs of developing infection. Normal healing produces mild redness and warmth during the first two days, but expanding redness that spreads beyond the original injury margin is abnormal. Increasing swelling, throbbing pain that intensifies rather than subsides, cloudy or foul-smelling drainage, and persistent heat indicate bacterial invasion. MedlinePlus emphasizes seeking medical attention for any signs of infection. Systemic warning signs like fever, chills, confusion, or red streaks traveling along a limb require urgent medical care.
Uncontrolled inflammation also raises the risk of hypertrophic scarring and contractures, especially when burns cross joints or skin folds. When healing is delayed, prolonged inflammatory signaling leads to excessive collagen deposition, creating thick, tight scar tissue that can permanently restrict range of motion. Early specialist follow-up guides tissue remodeling, mitigating contracture risk before long-term functional loss occurs.
What to Expect During Outpatient Burn Wound Care
Visiting a wound care specialist introduces an evidence-based, structured methodology to healing. Prior to starting any therapy, clinicians complete a rigorous diagnostic review. As outlined in the StatPearls clinical guide to wound assessment, practitioners examine the wound cause, anatomical location, and specific injury type before initiating treatment. A complete clinical assessment involves measuring length, width, and depth, evaluating for tissue undermining or tunneling, assessing the tissue types present in the wound bed, characterizing exudate volume and appearance, and inspecting the periwound skin for maceration or breakdown. These standardized measurements are repeated at subsequent visits to track objective healing trends and confirm that therapy remains appropriate.
Specialized treatments are customized to the clinical findings of each patient. Controlling moisture levels is essential; excessive wound drainage macerates neighboring skin, whereas a desiccated wound bed arrests cellular migration. Clinicians apply advanced moisture-retentive wound dressings—such as antimicrobial foams, hydrogels, or calcium alginates—to safeguard healing margins and optimize fluid balance.
For stalled, deep partial-thickness or complex injuries, clinicians may consider advanced modalities. Once a clean, vascularized wound base is achieved, providers evaluate appropriate candidates for cellular and tissue-based skin substitutes, which provide biological scaffolding to support cell proliferation, limit evaporative fluid loss, and encourage tissue regeneration. In select clinical environments, facilities equipped with hyperbaric chambers may provide hyperbaric oxygen therapy (HBOT) as an adjunct treatment for designated non-healing wounds, administering medical-grade oxygen at increased atmospheric pressures; however, HBOT is not appropriate for every burn injury and is always administered in a specialized hyperbaric chamber facility, never in a residential setting.
Personalized Support in Dallas–Fort Worth
Navigating recovery after a thermal injury requires diligent observation and compassionate clinical expertise. If your burn is healing slowly, causing worsening discomfort, or showing signs of infection, professional support can help. Schedule a specialized evaluation through our contact page today.
Sources
- MedlinePlus Medical Encyclopedia. Burns.
- Nagle SM, Stevens KA, Wilbraham SC. StatPearls Publishing, NCBI Bookshelf. Wound Assessment (StatPearls). 2023.